

October 7, 2026, 6:15 pm | Read time: 6 minutes
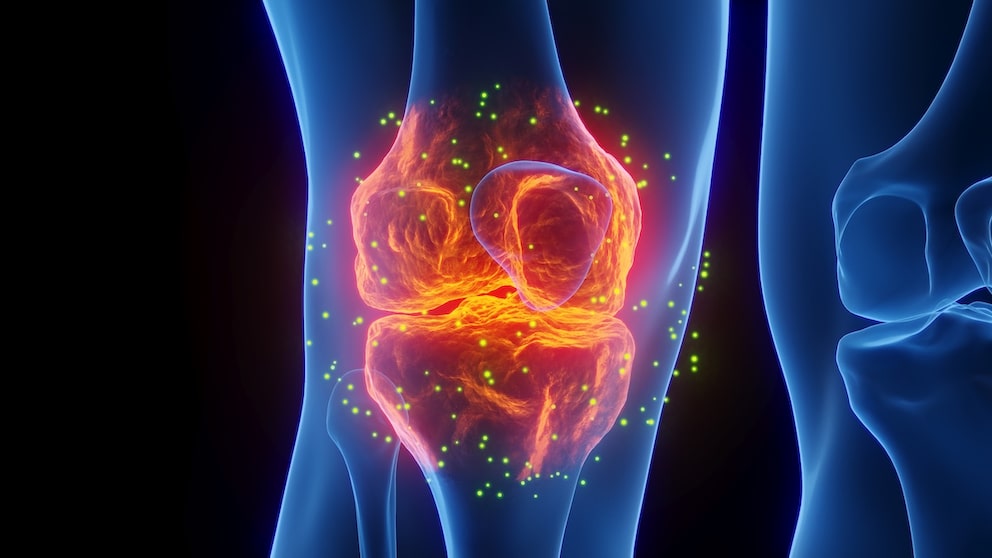
Osteoarthritis is one of the most common joint diseases and, according to current research, is not curable. The joint structures change, which can lead to significant symptoms such as pain and restricted movement. To reduce the risk of the disease and support joint function, targeted strength training and weight loss are recommended. South Korean researchers have now investigated whether alcohol consumption is associated with an increased risk of developing osteoarthritis. They identified a notable statistical correlation.
As FITBOOK explains in this article, various factors can contribute to the development of osteoarthritis. These include obesity, increasing age, genetic predisposition, previous joint injuries, and misalignments. Additionally, sustained high or unilateral stress on the joints can increase the risk. Conversely, lack of exercise can weaken muscles and further burden the joints.
Alcohol and Osteoarthritis
The role of alcohol as a potential factor in the development of osteoarthritis has been little studied. At the same time, it is known that its consumption can negatively affect existing osteoarthritis. One reason is that alcohol promotes silent inflammation in the body and disrupts important regeneration processes. Alcohol is also high in calories, which can contribute to obesity.
The authors of the current study investigated whether alcohol consumption is associated with a higher risk of osteoarthritis.1 They were particularly interested in whether a possible connection remains when two important accompanying factors are considered: obesity and liver diseases. They aimed to clarify whether these factors might explain any connection or if it remains independent of them.
Details of the Study
The study was a population-based cohort study. Unlike a randomized controlled trial, where participants are randomly assigned to different alcohol consumption groups, data from a large group of people were evaluated over a long period.
Data Collection
The researchers obtained data from the South Korean National Health Insurance Service (NHIS), the country’s state health insurance system. Adults aged 40 and older who participated in a health examination between 2009 and 2011 were included. The requirement was that no osteoarthritis was documented at the start of the observation. Ultimately, 1,233,179 participants with information on their alcohol consumption were included in the analysis. Their average age was 50.8 years.
To assess alcohol consumption, the authors relied on participants’ reports of their drinking frequency and estimated daily amount of ethanol, the alcohol found in alcoholic beverages. Based on this, participants were assigned to gender-specific consumption groups: “light alcohol consumption” (less than 10 grams of ethanol per day, roughly equivalent to a small glass of beer or soju), “moderate alcohol consumption” (10 to less than 30 grams per day for men and 10 to less than 20 grams for women), and “heavy alcohol consumption” (30 grams or more per day for men and 20 grams or more for women). The comparison group consisted of people who did not drink alcohol.
To evaluate whether liver diseases or obesity could explain any connections, the researchers separately considered people with normal liver function and no known liver disease, as well as people with normal weight and no history of obesity.
Participants were followed until a first diagnosis of osteoarthritis (based on billing data) or their death, with official follow-up running until December 31, 2023. Osteoarthritis resulting from injury was excluded.
Analysis
For the analysis, the researchers compared the osteoarthritis risk of the different alcohol groups. They considered additional factors that could influence the risk. The results were presented as hazard ratios (HR). A value of 1 indicates that the groups do not differ in terms of risk. Values above 1 indicate a higher risk.
Results: More Alcohol, Higher Osteoarthritis Risk
During the average 9.9-year follow-up period, 571,077 participants were diagnosed with osteoarthritis for the first time. A clear pattern emerged: The more alcohol consumed, the higher the rate of newly developed osteoarthritis.
Compared to non-drinkers, the rate
- was 3.7 percent higher for light alcohol consumption,
- 8.1 percent higher for moderate alcohol consumption,
- 18.6 percent higher for heavy alcohol consumption.
The connection remained even when the researchers excluded people with liver diseases or impaired liver function, as well as those with obesity or a history of obesity, from the respective analyses.
Women May Be More Sensitive to Alcohol
The researchers noted a difference between genders. In women, a connection with increased osteoarthritis occurrence was already evident at lower alcohol amounts than in men: While men with light consumption showed no increased osteoarthritis risk, women in the light consumption group (under 10 grams of ethanol per day) had a 6.3 percent increased risk.
Even One Drink Can Increase Cancer Risk

Men More Often Affected by Cancer: Study Identifies Key Factors
Significance of the Results
According to the analysis, alcohol consumption in the large South Korean population group studied was associated with a higher rate of newly diagnosed osteoarthritis. The statistical connection was stronger with increasing consumption. The findings from groups with normal liver function and normal weight also suggest that the observed link cannot be solely explained by liver problems or obesity.
However, it is important to note that the numbers only show a statistical connection. They do not indicate that 18.6 percent of heavy drinkers develop osteoarthritis or that alcohol is the proven cause of the disease.
Nevertheless, people interested in their joint health–possibly women in particular–might take the study as an opportunity to at least consider their alcohol consumption more closely. Although the results do not provide a solid indication that reducing or abstaining from alcohol would prevent osteoarthritis or improve its course. Such a statement requires further studies that specifically examine whether a change in consumption affects the risk of the disease.
Two central questions arise for the next research steps: What mechanisms could explain the connection, and does it persist in other population groups? Experimental studies suggest that acetaldehyde–a breakdown product of ethanol–as well as oxidative stress and inflammatory signals could damage cartilage cells and activate cartilage-degrading enzymes.
Also interesting: What Alcohol Does to the Bodies of Children and Adolescents
Limitations
As an observational study, the investigation cannot prove that alcohol causes the disease. Even statistical consideration of additional influencing factors cannot rule out that other, unrecorded factors contribute to the result. The study authors did, however, consider a variety of key variables in their statistical models, such as age, BMI, blood pressure, fasting blood sugar, cholesterol, smoking, physical activity, income, and comorbidities (such as diabetes, hypertension, and dyslipidemia).
Another limitation concerns the assessment of alcohol consumption. Participants self-reported their drinking frequency and estimated daily alcohol amount. Such reports can deviate from actual consumption–not only due to memory gaps. Additionally, the formed consumption groups do not allow for conclusions on how a specific drinking amount precisely affects individual osteoarthritis risk.
Limitations are also noted regarding the assessment of the disease. Only documented osteoarthritis diagnoses were considered. Unrecorded or yet-to-be-diagnosed joint diseases were excluded from the analysis.
The data referred to adults aged 40 and older in South Korea. Thus, it remains open whether the observations can be transferred to other population groups. While the connection persisted among individuals with normal liver function and normal weight, it is insightful but does not exclude other possible influencing factors and does not prove a direct causal link between alcohol and osteoarthritis.